


Cervical Spondylomyelopathy
Cervical spondylomyelopathy, also called cervical vertebral malformation-malarticulation and wobbler syndrome, is a clinical syndrome arising from compression of the spinal cord caused by abnormal development of the cervical vertebrae. Genetic factors and possibly nutrition might be involved.
Dogs can exhibit two forms of cervical spondylomyelopathy:
Disk-associated wobbler syndrome affects middle-aged large-breed dogs, especially Doberman Pinschers (typical age of onset: 7 years). Protrusion of one or more caudal cervical intervertebral disks causes ventral compression of the spinal cord. Some cases are complicated by congenital stenosis of the vertebral canal or hypertrophy of the ligamentum flavum.
Bony-associated cervical spondylomyelopathy affects young giant-breed dogs, including Great Danes, Mastiffs, and Rottweilers (age range: several months to 4 years). Spinal cord compression is due to bony proliferation of the articular processes and pedicles, usually of the C4-C7 vertebrae.
Clinical signs of cervical spondylomyelopathy can be acute or slowly progressive. Mild cases are characterized by subtle ataxia of all limbs, often evident as a long, protracted stride in the pelvic limbs, with a short-strided gait in the thoracic limbs (sometimes called a two-engine gait). In severe cases, paresis or paralysis of all limbs can occur. Neck pain is variable.
Differential diagnoses for cervical spondylomyelopathy include the following:
congenital anomalies
trauma
meningomyelitis
neoplasia
Survey radiographs cannot confirm a diagnosis of cervical spondylomyelopathy; however, they are useful in identifying vertebral abnormalities and excluding diskospondylitis and bony neoplasia. Definitive diagnosis requires myelography, CT, or MRI (see , and ).

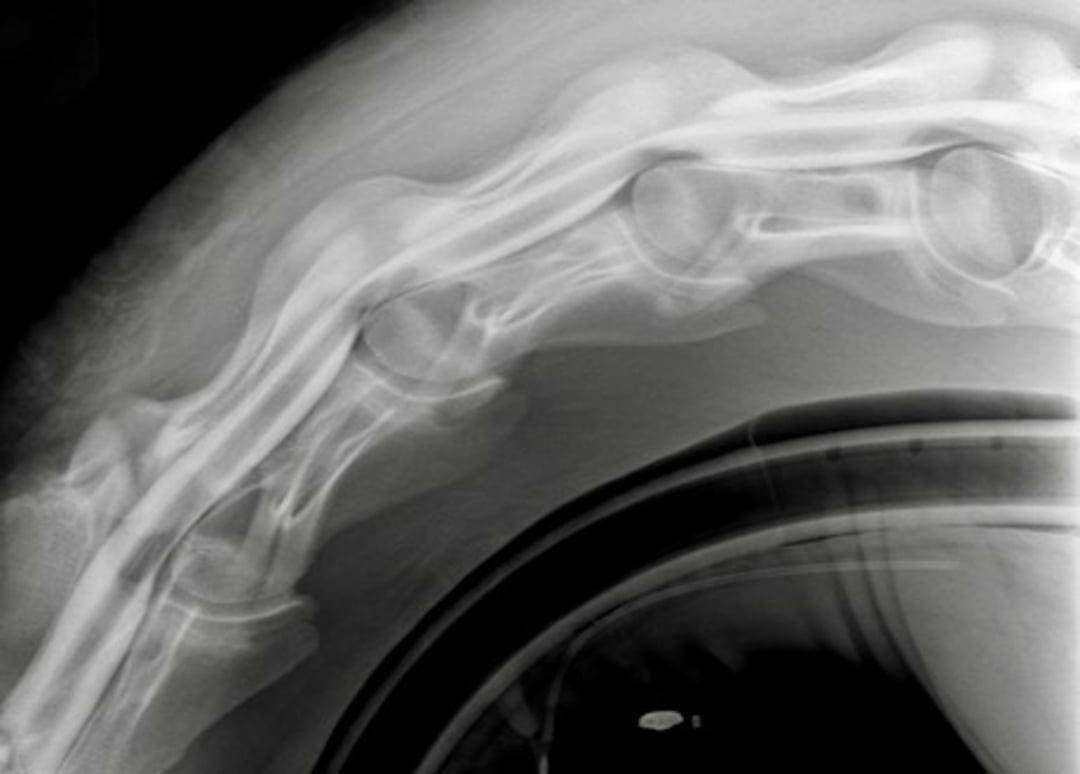
Lateral myelogram of a horse with wobbler syndrome, showing attenuation of the ventral contrast column at the level of C3-C4 and C4-C5.
Courtesy of Dr. William Thomas.

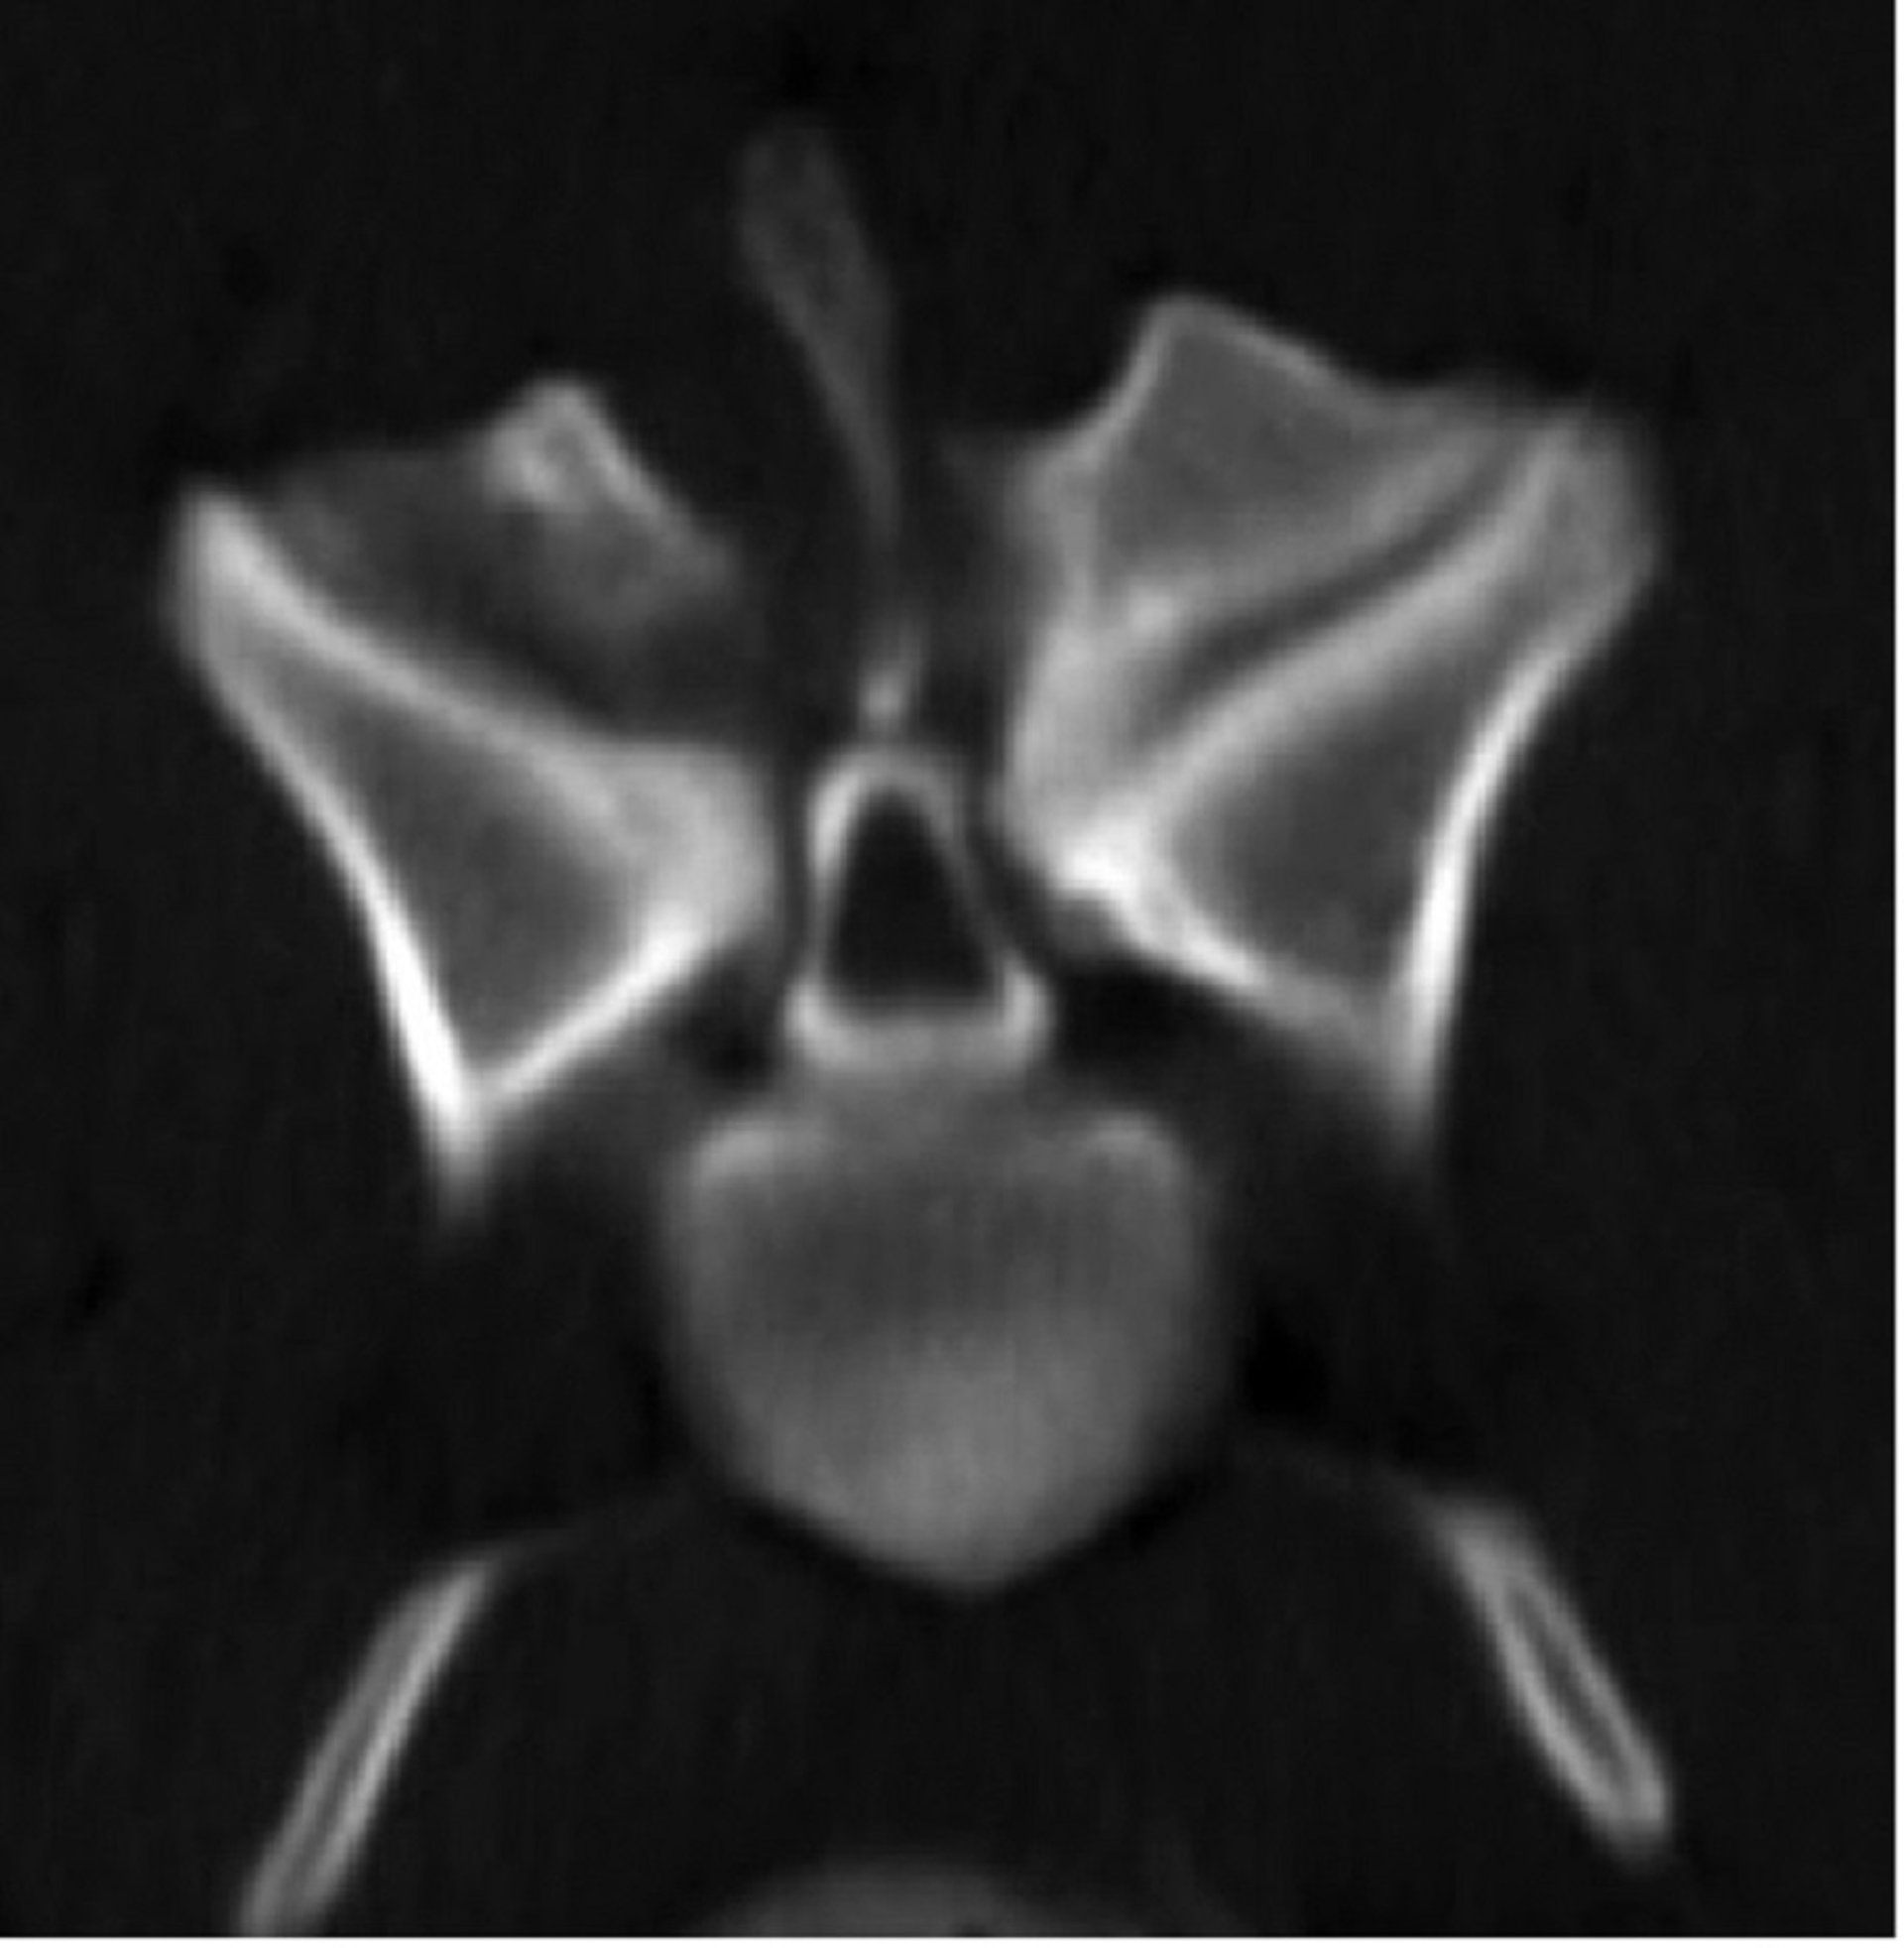
CT myelogram of a dog, showing compression of the spinal cord associated with bilateral articular facet enlargement.
Courtesy of Dr. William Thomas.
Nonsurgical treatment of cervical spondylomyelopathy is indicated for dogs with mild clinical signs and consists of exercise restriction, prednisone (0.5 mg/kg, PO, every 24 hours, tapered slowly over months to years), and, if necessary, weight loss (1). Clinical signs improve in approximately 50% of dogs and remained unchanged in approximately 25% of dogs with nonsurgical treatment (1).
Surgery is indicated in dogs with substantial neurological deficits and in those that do not respond adequately to nonsurgical treatment. The choice of technique is based on the changes evident on imaging; surgical techniques include ventral slot procedure with partial diskectomy, dorsal laminectomy, distraction and fusion of affected vertebrae, and placement of an artificial disk. Overall, approximately 80% of dogs do well with surgery (2).
In horses, cervical spondylomyelopathy is the most common noninfectious disease of the spinal cord and occurs in many breeds. Most affected horses develop clinical signs at < 3 years old; however, they can be affected at any age.
The midcervical region is most commonly affected, and proprioceptive ataxia and tetraparesis occur. Handler and rider safety is a major concern in horses with ataxia.
Diagnosis of cervical spondylomyelopathy in horses is based on imaging and excluding other causes. Plain radiographs might show abnormal articular facets and stenosis of the vertebral canal. Myelography is necessary for definitive diagnosis and surgical planning.
Surgery most commonly involves ventral fusion of the affected vertebrae. Nonsurgical treatment involves NSAIDs and dimethyl sulfoxide to decrease inflammation. In yearlings, diet modification might help, including feeding only grass hay or pasture with no grain and supplementing with a ration balancer to ensure adequate protein and mineral intake (3).
Degenerative Lumbosacral Stenosis
Narrowing of the lumbosacral vertebral canal or intervertebral foramina results in compression of the cauda equina or nerve roots. It is most common in large breeds of dogs, especially German Shepherd Dogs, and is rare in cats.
Degenerative lumbosacral stenosis results from degeneration and protrusion of the L7-S1 disk, hypertrophy of the ligamentum flavum, or, rarely, subluxation of the lumbosacral joint. The cause is unknown; however, German Shepherd Dogs with congenital transitional vertebrae are at increased risk.
Clinical signs of degenerative lumbosacral stenosis typically begin at 3–7 years old and can include difficulty using the pelvic limbs, pelvic limb lameness, tail weakness, and incontinence. Pain on palpation or extension of the lumbosacral joint is the most consistent finding. Proprioceptive deficits, muscle atrophy, or a weak flexor reflex in the pelvic limbs might be present.
Plain radiographs can show degenerative changes; definitive diagnosis, however, requires MRI, CT, or epidurography (see ). Dogs in which mild pain is the only clinical sign might improve with 4–6 weeks of rest. Epidural injection of methylprednisolone acetate (1 mg/kg on each of day 1, day 14, and day 42) is effective in approximately 80% of dogs with pain and minimal neurological deficits (4).

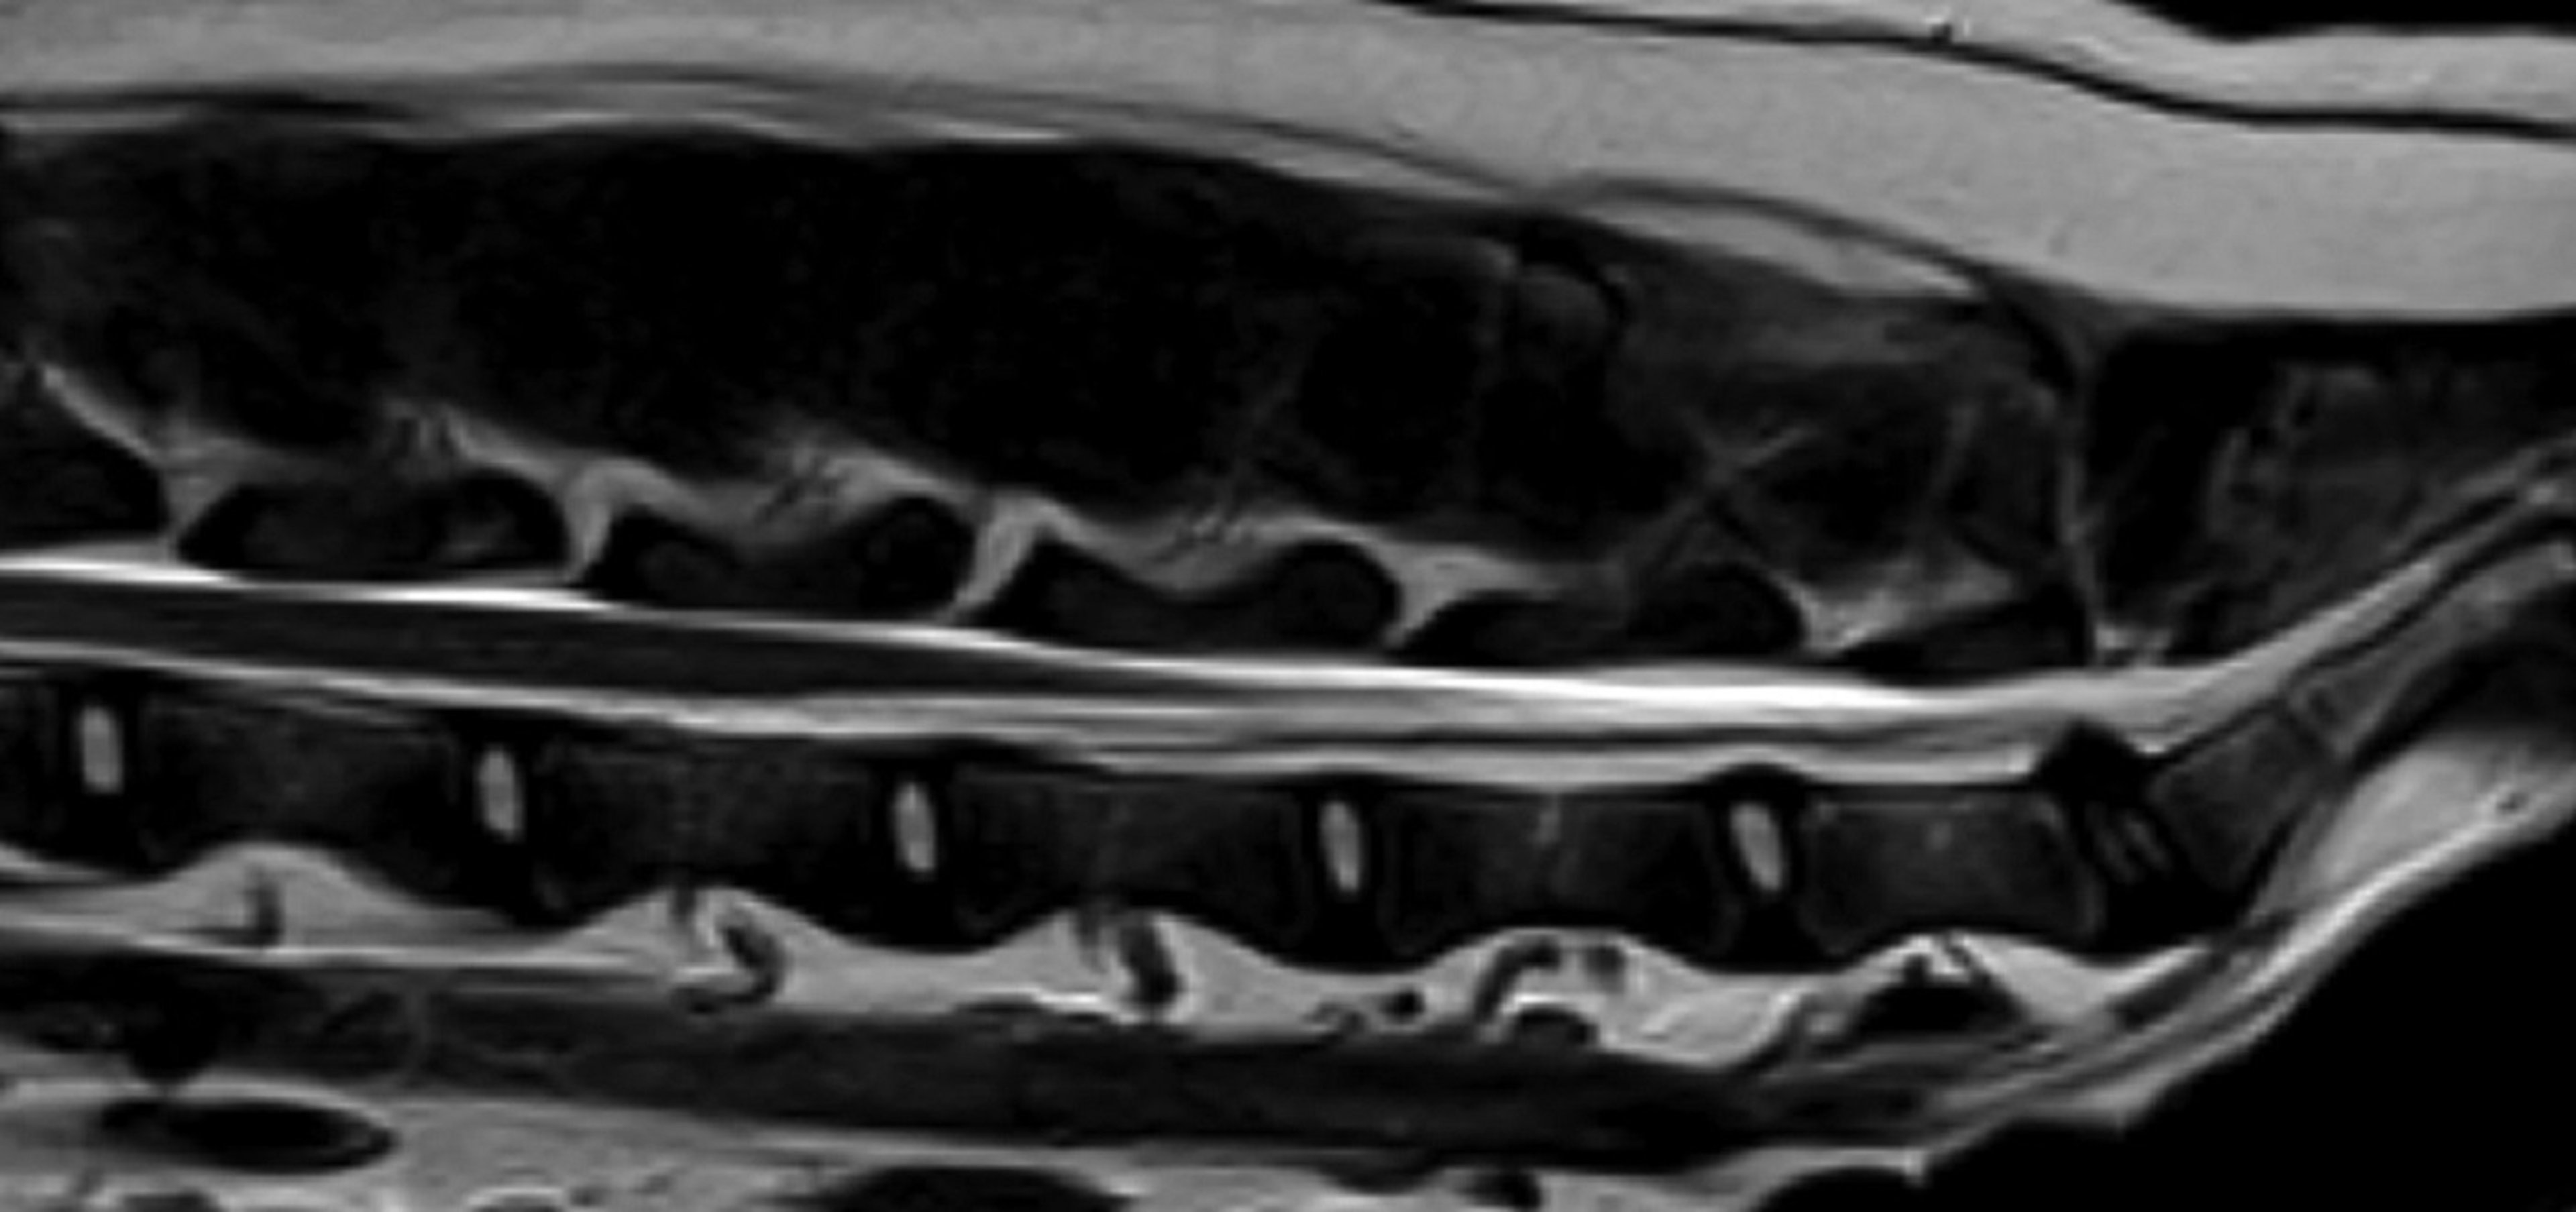
Sagittal plane T2-weighted MRI image of a dog, showing L7-S1 disk protrusion compressing the cauda equina.
Courtesy of Dr. William Thomas.
Surgery is indicated when pain is refractory to medical treatment or there are neurological deficits. The most common surgical technique is dorsal laminectomy with partial diskectomy; however, foramenotomy or stabilization is indicated in certain cases. Approximately 70–95% of dogs improve with surgery; however, preexisting urinary incontinence might not resolve (5). (See and of lumbosacral stabilization.)


Postoperative lateral radiographic view showing stabilization of the lumbosacral joint using pedicle screws and rods.
Courtesy of Dr. William Thomas.


Postoperative 3D CT reconstruction showing lumbosacral stabilization using pedicle screws and rods.
Courtesy of Dr. William Thomas.
Degenerative Myelopathy of Dogs
Degenerative myelopathy of dogs, also called chronic degenerative radiculomyelopathy, is a slowly progressive, noninflammatory degeneration of the axons and myelin primarily affecting the white matter of the spinal cord. It is most common in German Shepherd Dogs, Pembroke Welsh Corgis, Boxers, Rhodesian Ridgebacks, and Chesapeake Bay Retrievers; however, it is occasionally recognized in many other breeds.
Degenerative myelopathy is associated with a mutation in the superoxide dismutase 1 (SOD1) gene, inherited in an autosomal recessive pattern with incomplete penetrance. Dogs that are homozygous for the mutation are at risk of the disease and will pass one copy of the mutant allele to their offspring. Heterozygotes are at low risk of the disease; however, they have a 50% chance of passing one copy of the mutant allele to each offspring (6). Dogs that are homozygous for the normal allele are at low risk of developing SOD1-associated degenerative myelopathy and will not pass the mutation to offspring.
The disease is considered analogous to familial amyotrophic lateral sclerosis in human patients. Pathologically, noninflammatory degeneration of axons in the white matter of the spinal cord occurs, which is most severe in the thoracic region.
Affected dogs are usually > 8 years old and develop an insidious onset of nonpainful ataxia and weakness of the pelvic limbs. Spinal reflexes are usually normal or exaggerated; in advanced cases, however, flaccid tetraparesis and hyporeflexia reflect lower motor neuron involvement. Early cases can be confused with orthopedic disorders; however, proprioceptive deficits are an early feature of degenerative myelopathy and are not evident in orthopedic disease.
Myelography or MRI and CSF analysis are useful to exclude compressive and inflammatory diseases. A DNA test based on the SOD1 gene is available from the Orthopedic Foundation for Animals.
There is no specific treatment for degenerative myelopathy and no evidence that glucocorticoids, other drugs, or supplements alter the course of the disease. Most affected dogs are euthanized because of disability within 1–3 years after diagnosis.
Degenerative Myeloencephalopathy in Horses
Equine degenerative myeloencephalopathy, also called equine neuroaxonal dystrophy, is a progressive neurological disorder of horses and zebras characterized by diffuse degeneration of axons, myelin, and neurons in the spinal cord and, to a lesser extent, the brainstem.
Equine degenerative myeloencephalopathy has been reported in many equine breeds in North America, Australia, and England. The cause is incompletely understood; however, vitamin E deficiency and genetic factors are likely.
Clinical signs of equine degenerative myeloencephalopathy usually become apparent before 1 year of age and consist of ataxia and weakness in all four limbs; however, the pelvic limbs might be more severely affected. Clinical signs can stabilize or slowly progress.
No definitive diagnostic test exists for equine degenerative myeloencephalopathy. Clinical diagnosis is based on clinical features and excluding other causes. Results of myelography and CSF analysis are normal.
Preventive measures include ensuring access to lush, green pasture for mares and for young horses up to 2 years old to ensure adequate dietary vitamin E. Supplementation of pregnant mares and newborn foals with vitamin E is preventive in predisposed families. The dam's serum alpha-tocopherol concentrations can determine the need for supplementation during pregnancy and lactation. For foals, the serum alpha-tocopherol concentration should be evaluated within the first week after birth to determine the need for supplementation.
Once neurological signs develop, supplementation can prevent worsening; however, treatment does not reverse neurological deficits.
Intervertebral Disk Disease
Degeneration and subsequent herniation of the intervertebral disk results in spinal cord, spinal nerve, or nerve root compression, a common cause of spinal cord disease in dogs, with alifetime prevalence of approximately 3.5% (7).
Clinical signs of disk disease are rare in cats and horses. Chondrodystrophoid breeds of dogs (eg, Dachshund, French Bulldog, Beagle, Shih Tzu, Lhasa Apso, and Pekingese) are most commonly affected, with Miniature Dachshunds having a lifetime prevalence of approximately 20% (8). In these breeds, chondroid degeneration of the disks occurs within the first few months of life. Disk extrusion can occur as early as 1–2 years of age, and clinical signs are often acute and severe.
Two fibroblast growth factor 4 (FGF4) retrogenes—one on Canis familiaris chromosome (CFA) 18 and one on CFA 12—contribute to the chondrodystrophoid phenotype, with the FGF4 on CFA 12 drastically increasing the risk of disk degeneration.
Large-breed dogs can suffer fibroid disk degeneration as they age. This type of degeneration predisposes affected dogs to a slowly progressive protrusion of the disk. Clinical signs of intervertebral disk disease typically develop at > 5 years old and consist of slowly progressive ataxia and paresis.
A third type of intervertebral disk herniation is acute extrusion of a healthy, nondegenerate disk, which occurs most commonly during exercise in relatively young dogs. In some cases the extruded disk material compresses the spinal cord or even penetrates the dura mater or spinal cord. In other cases, the volume of extruded disk material is so small that it does not cause any persistent compression; however, the velocity of extrusion causes a concussive injury to the spinal cord, a syndrome referred to as acute noncompressive nucleus pulposus extrusion.
The most common sites of disk herniation are the cervical and thoracolumbar regions. The predominant clinical sign of cervical disk herniation is neck pain, manifested as cervical rigidity and muscle spasms. Thoracic limb lameness (nerve root signature) or neurological deficits, ranging from mild tetraparesis to tetraplegia, might be present.
Thoracolumbar disk herniation can include back pain, evident as kyphosis and reluctance to move. Neurological deficits are usually more severe than those that occur in cervical disk disease and range from pelvic limb ataxia to paraplegia and incontinence.
In paraplegic animals, the most important prognostic finding is whether there is deep pain perception caudal to the lesion. This is assessed by pinching the toe or tail and observing whether there is a behavioral response, such as a bark or turn of the head. It is important to pinch the bone to stimulate deep pain receptors, not just the skin, which tests only superficial pain. Reflex flexion of the limb must not be mistaken for a behavioral response.
Pearls & Pitfalls
|
Definitive diagnosis of disk extrusion is based on imaging studies. Spinal radiographs might show narrowing of the affected disk space, intervertebral foramen or articular facets, or radiodense calcified disk material within the vertebral canal. However, radiographs are not sensitive or specific enough for definitive diagnosis, which requires myelography, MRI, or CT. (See intervertebral disk extrusion images [ and ] and .)


Transverse plane T2-weighted MRI image of a dog with intervertebral disk extrusion, showing compression of the left lateral aspect of the spinal cord.
Courtesy of Dr. William Thomas.


Sagittal CT image of a dog with intervertebral disk extrusion, showing calcified disk extrusion at C3-C4.
Courtesy of Dr. William Thomas.


T2-weighted sagittal MRI image of a dog with intervertebral disk extrusion showing extrusion of the C6-C7 intervertebral disk with compression of the spinal cord.
Courtesy of Dr. William Thomas.
Dogs with pain and minimal to moderate neurological deficits often recover with 2–3 weeks of cage rest. A short course of prednisone (0.5 mg/kg, PO, every 24 hours for 3 days) is often helpful in relieving pain (8); however, no evidence exists that steroids or any other drugs improve neurological recovery. The use of anti-inflammatory or analgesic medication without concurrent cage rest is contraindicated because an increase in the dog’s activity might lead to further disk extrusion and worsening of spinal cord compression. Clinical signs recur after conservative treatment in 30–40% of cases (9).
In animals with severe neurological deficits, prompt surgery offers the best chance of recovery in patients with appreciable spinal cord compression (see the table ).
Recovery Rates After Surgery for Intervertebral Disk Disease in Dogs
Patient Type | Recovery Rate |
|---|---|
Nonambulatory small-breed dog with thoracolumbar extrusion and intact deep pain | 85–95% |
Small-breed dog with thoracolumbar extrusion and loss of deep pain < 24 hours | 50% |
Small-breed dog with thoracolumbar extrusion and loss of deep pain > 24 hours | < 50% |
Nonambulatory large-breed dog with chronic thoracolumbar protrusion | 25–50% |
Ambulatory dog with cervical disk disease | 95% |
Nonambulatory dog with cervical disk disease | 65–95% |
Brisson BA. Intervertebral disc disease in dogs. Vet Clin North Am Small Anim Pract. 2010;40(5):829-858. doi:10.1016/j.cvsm.2010.06.001 | |
Other indications for surgery to treat intervertebral disk disease are failure of conservative treatment and recurrent episodes.
For cervical disk extrusion, a ventral slot procedure is the most common. Hemilaminectomy with removal of the extruded disk material is the most common procedure for thoracic or lumbar extrusions. Prophylactic fenestration of commonly affected disk spaces (eg, T11 through L4) decreases recurrence in small-breed dogs.
Following an acute intervertebral disk extrusion with paraplegia and loss of deep pain perception, some dogs (approximately 5–10%) develop progressive myelomalacia, a complication characterized by progressive ascending and descending necrosis of the spinal cord (10, 11, 12). In this syndrome, affected dogs develop flaccid tetraplegia, cranial migration of cutaneous trunci reflex, and fatal respiratory paralysis.
Fenestration of the commonly affected disk spaces at the time of surgery decreases the risk of future extrusion (13). Other techniques, such as percutaneous laser disk ablation and chemonucleolysis, have been used to decrease recurrence and, less commonly, to treat acute extrusions (14); however, controlled clinical trials are lacking.
Diffuse Idiopathic Skeletal Hyperostosis in Dogs
Also known as Forestier disease in human patients, diffuse idiopathic skeletal hyperostosis (DISH) is characterized by ossification of entheses, the sites where a ligament, tendon, or joint capsule inserts into bone.
Radiographic criteria for diagnosis are flowing ossification along the ventrolateral aspect of at least four contiguous vertebrae with relative preservation of disk width and absence of facet joint ankylosis (see ).

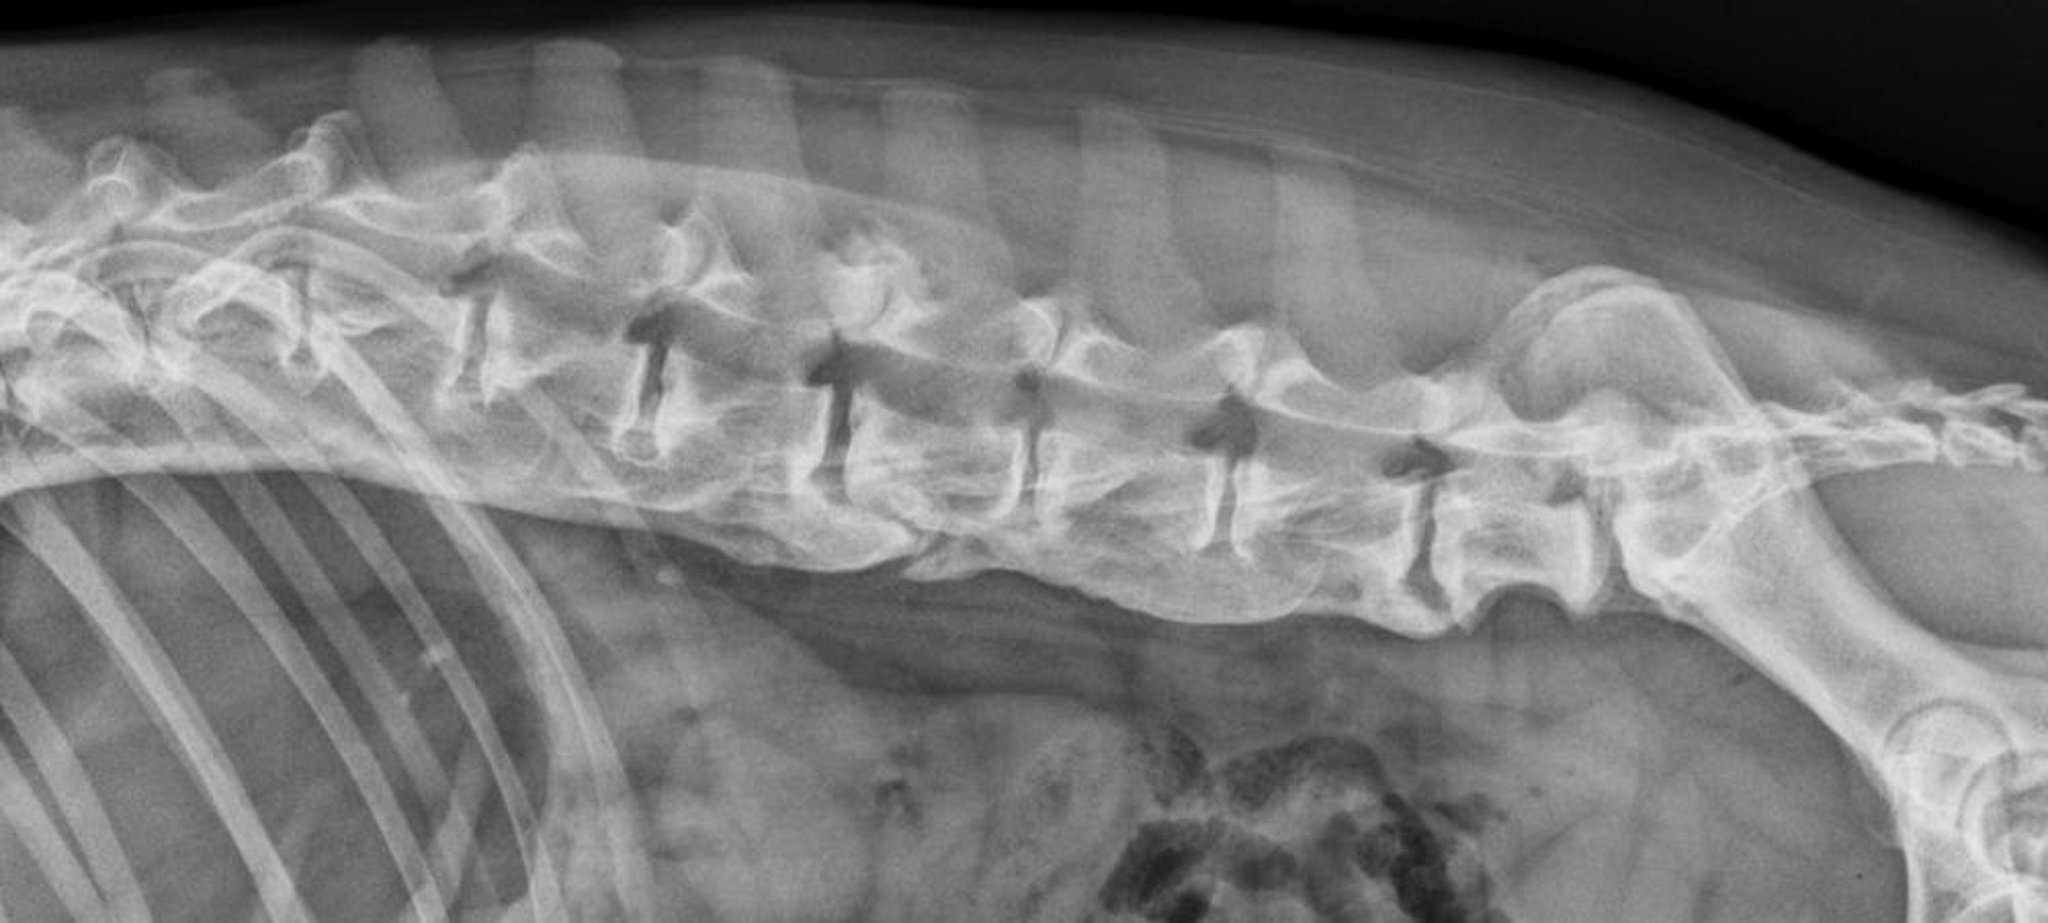
Lateral radiographic view of a dog with diffuse idiopathic skeletal hyperostosis (DISH). There is flowing ossification along the ventral aspect of most of the vertebral bodies.
Courtesy of Dr. William Thomas.
Approximately 4% of dogs > 1 year old are affected with DISH, and prevalence increases with age. As with spondylosis deformans, Boxers are at increased risk, with a prevalence of approximately 40% (15). The thoracic and lumbar regions are most commonly affected.
It is unclear how often DISH causes clinical signs, and in many cases the radiographic findings are incidental. However, spinal pain and stiffness are possible, and in those cases, treatment involves analgesics as needed.
Motor Neuron Disease in Horses
Equine motor neuron disease is a progressive, noninflammatory degeneration of motor neurons in the spinal cord and brainstem of horses.
Equine motor neuron disease is most common in the northeastern US; however, it has been reported in several areas of North and South America, Europe, and Japan. The cause is uncertain, but vitamin E deficiency is a strong risk factor. Adult horses of any age and breed can be affected, although Quarter Horses are affected most commonly. Affected horses typically do not have access to pasture grass and are fed poor-quality grass hay.
Clinical signs of equine motor neuron disease consist of generalized symmetrical weakness, trembling, and muscle atrophy. Affected horses often stand with their head held low and their feet camped under their body, frequently shifting their weight from one limb to another. Ataxia is not a feature of this disease, in contrast to most spinal cord diseases. Many affected horses have retinal abnormalities, including a distinct reticulated pigment pattern and areas of hyperreflectivity.
Electromyography and biopsy of the spinal accessory nerve or the sacrocaudalis dorsalis medialis muscle are useful in diagnosis.
No specific treatment exists for equine motor neuron disease; however, some horses improve partially after 2–3 months of illness.
To prevent deficiency, horses that lack access to green forage high in vitamin E for prolonged periods should be supplemented with vitamin E.
Degeneration of Motor Neurons
Degeneration of motor neurons is an inherited or sporadic disease that occurs in Brittany Spaniels, Pointers, German Shepherd Dogs, Doberman Pinschers, and Rottweilers; cats; Hereford, Brown Swiss, and Danish Red cattle; Yorkshire pigs; and goats. Also called spinal muscular atrophy, this disease is characterized by progressive paresis, tremor, muscle atrophy, and weak spinal reflexes. The age of onset is typically within the first 1−2 years of life.
Electromyography and muscle biopsy help document muscle denervation; definitive diagnosis, however, is based on loss of motor neurons in the ventral horn of the spinal cord and brainstem nuclei on necropsy.
Metabolic Storage Disorders
Rare, usually inherited, metabolic disorders can affect the CNS, including the spinal cord. (Also see Congenital and Inherited Anomalies of the Nervous System.)
Spondylosis Deformans
Spondylosis deformans is a noninflammatory condition characterized by formation of bony projections (enthesophytes) at the location where the annulus fibrosus is attached to the cortical surface of adjacent vertebrae. These bony growths vary from small spurs located several millimeters from the junction between the disk and vertebra to bony bridges that span the disk space, leaving at least part of the ventral surface of the vertebra unaffected (see ). The enthesophytes typically expand laterally and ventrally but not dorsally; therefore, they rarely affect the spinal cord.
The cause of spondylosis deformans is breakdown of the outer fibers of the annulus fibrosis and stretching of the longitudinal ligament. The increased stress at the vertebral attachment of the longitudinal ligament incites bony production.


Lateral radiographic view of a German Shepherd Dog with spondylosis deformans. There is smooth, new bone formation on the ventral aspect of the vertebral end plates adjacent to the intervertebral disk. This was an incidental finding; the cause of the dog's paraparesis was degenerative myelopathy.
Courtesy of Dr. William Thomas.
Spondylosis deformans occurs in dogs, cats, and bulls, and the incidence increases with age. It is uncommon in dogs < 2 years old; by 9 years old, 25–70% of all dogs are affected (1). The condition is especially common in Boxers, and a genetic predisposition has been identified in this breed.
Spondylosis deformans is typically an incidental radiographic finding, and no correlation exists between the presence of spondylosis and clinical signs. Rare cases cause spinal hyperesthesia, which should be treated with analgesics.
For More Information
What is Degenerative Myopathy? University of Missouri College of Veterinary Medicine.
Olby NJ, Moore SA, Brisson B, et al. ACVIM consensus statement on diagnosis and management of acute canine thoracolumbar intervertebral disc extrusion. J Vet Intern Med. 2022;36(5):1570-1596.
References
da Costa RC. Cervical spondylomyelopathy (wobbler syndrome) in dogs. Vet Clin North Am Small Anim Pract. 2010;40(5):881-913. doi:10.1016/j.cvsm.2010.06.003
da Costa RC, Parent JM, Holmberg DL, Sinclair D, Monteith G. Outcome of medical and surgical treatment in dogs with cervical spondylomyelopathy: 104 cases (1988-2004). J Am Vet Med Assoc, 2008;233(8):1284-1291. doi:10.2460/javma.233.8.1284
Hoffman CJ, Clark CK. Prognosis for racing with conservative management of cervical vertebral malformation in thoroughbreds: 103 cases (2002-2010). J Vet Intern Med. 2013;27(2):317-323. doi:10.1111/jvim.12053
Janssens L, Beosier Y, Daems R. Lumbosacral degenerative stenosis in the dog: the results of epidural infiltration with methylprednisolone acetate: a retrospective study. Vet Comp Orthop Traumatol. 2009;22(6):486-491. doi:10.3415/VCOT-08-07-0055
Danielsson F, Sjöström L. Surgical treatment of degenerative lumbosacral stenosis in dogs. Vet Surg. 1999;28(2):91-98. doi:10.1053/jvet.1999.0091
Coates JR, Wininger FA. Canine degenerative myelopathy. Vet Clin North Am Small Anim Pract. 2010;40(5):929-950. doi:10.1016/j.cvsm.2010.05.001
Bergknut N, Egenvall A, Hagman R, et al. Incidence of intervertebral disk degeneration-related diseases and associated mortality rates in dogs. J Am Vet Med Assoc. 2012;240(11):1300-1309. doi:10.2460/javma.240.11.1300
Mann FA, Wagner-Mann CC, Dunphy ED, Ruben DS, Rochat MC, Bartels KE. Recurrence rate of presumed thoracolumbar intervertebral disc disease in ambulatory dogs with spinal hyperpathia treated with anti-inflammatory drugs: 78 cases (1997–2000). J Vet Emerg Crit Care (San Antonio), 2007;17(1):53-60. doi:10.1111/j.1476-4431.2006.00195.x
Levine JM, Levine GJ, Johnson SI, Kerwin SC, Hettlich BF, Fosgate GT. Evaluation of the success of medical management for presumptive thoracolumbar intervertebral disk herniation in dogs. Vet Surg. 2007;36(5):482-491. doi:10.1111/j.1532-950X.2007.00295.x
Aikawa T, Fujita H, Kanazono S, Shibata M, Yoshigae Y. Long-term neurologic outcome of hemilaminectomy and disk fenestration for treatment of dogs with thoracolumbar intervertebral disk herniation: 831 cases (2000-2007). J Am Vet Med Assoc. 2012;241(12):1617-1626. doi:10.2460/javma.241.12.1617
Olby NJ, Muguet-Chanoit AC, Lim JH, et al. A placebo-controlled, prospective, randomized clinical trial of polyethylene glycol and methylprednisolone sodium succinate in dogs with intervertebral disk herniation. J Vet Intern Med. 2016;30(1):206-214. doi:10.1111/jvim.13657
Olby N, Levine J, Harris T, Muñana K, Skeen T, Sharp N. Long-term functional outcome of dogs with severe injuries of the thoracolumbar spinal cord: 87 cases (1996-2001). J Am Vet Med Assoc. 2003;222(6):762-769. doi:10.2460/javma.2003.222.762
Brisson BA, Holmberg DL, Parent J, Sears WC, Wick SE. Comparison of the effect of single-site and multiple-site disk fenestration on the rate of recurrence of thoracolumbar intervertebral disk herniation in dogs. J Am Vet Med Assoc. 2011;238(12):1593-1600. doi:10.2460/javma.238.12.1593
Bartels K. Use of lasers in veterinary surgery and percutaneous laser disc ablation. In: Fingeroth JM, Thomas WB, eds. Advances in Intervertebral Disc Disease in Dogs and Cats. Wiley-Blackwell; 2015:268-278. doi:10.1002/9781118940372.ch37
Thomas WB, Fingeroth JM. Spondylosis deformans. In: Fingeroth JM, Thomas WB, eds. Advances in Intervertebral Disc Disease in Dogs and Cats. Wiley-Blackwell; 2015:67-74. doi:10.1002/9781118940372.ch8







